Introduction
Spontaneous haemoperitoneum is a rare life-threatening condition which is defined as a non-iatrogenic and non-traumatic aetiology of blood within the peritoneal cavity [1]. Despite modern imaging techniques pre-operative diagnosis is challenging with delays contributing to the high associated mortality rate [2]. There are multiple described possible sources of bleeding including visceral, coagulopathy-related, gynaecologic, and vascular [1]. Vascular causes include rupture of an aneurysm, pseudoaneurysm, or Arteriovenous Malformation (AVM) [2].
Case presentation
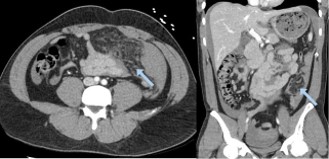
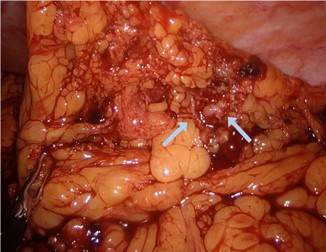
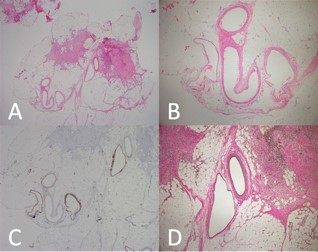
We report the case of a normally fit and well 33-year-old Māori male who presented with a 48 hour history of sudden onset generalised abdominal pain. Four-days prior he had a brief period of sharp abdominal pain after recording a solo martial arts demonstration video. It was clarified on multiple occasions there was no blunt force trauma to any part of the body. He does not smoke, takes no regular medications and drinks alcohol socially. His observations were normal on presentation apart from mild tachycardia and his initial haemoglobin was 150 g/L, white blood cells 17.3×^10/L and his lactate was 2.7 mmol/L. Clinical examination findings were of generalised abdominal pain with peritonism. Worsening pain and a repeat Hb demonstrated a 30 point haemoglobin drop to 120 g/L within four hours of observation in the emergency department prompted an urgent contrast CT scan which demonstrated moderate volume haemoperitoneum, with a large haematoma in the left abdomen and pelvis; omental and mesenteric stranding with no cause of the bleeding identified (Figure 1). A decision was made to proceed with diagnostic laparoscopy. Intraoperative findings were of a large volume hemoperitoneum centred around abnormally vascular appearing omentum in the left lower quadrant (Figure 2). No other intra-abdominal bleeding sources were identified. The bleeding abnormal omentum was widely respected using a LigaSure energy device and sent for pathological examination. He required one unit of red blood cell transfusion and his post-operative haemoglobin was 80 g/L. His post-operative course was uncomplicated and he was discharged on day 3 post-operatively. The pathology report was consistent with omental AVM (Figure 3).
Discussion
Omental AVM is a rare cause of spontaneous hemoperitoneum with four prior case reports in the literature [1-4]. As with our case report, none were diagnosed pre-operatively despite the use of a CT scan in all cases. This reflects the diagnostic challenge posed by the condition and highlights the importance of clinical awareness, as the diagnosis is typically made intra-operatively.
This is the first case report of successful minimally invasive management of a spontaneously bleeding omental AVM. All prior case reports required a laparotomy for definitive management. A laparoscopic approach is only feasible when the patient is haemodynamically stable, there is no obvious evidence of solid organ injury, and there is an absence of significant trauma history. Pre-existing awareness of this rare pathology can prevent the omentum from being overlooked as a potential bleeding source during exploration, leading to prolonged operative time or conversion to open surgery in search of an alternative aetiology.
Acknowledgements: Dr Stephen Allpress, for his help with the pathology images.
References
- Lovitskyi Y, Romanenko Y, Shcherbyna M, Zadorozhna K, Kalyna R, Herasymenko E, et al. Unusual spontaneous intraperitoneal hemorrhage: three case reports. J Surg Case Rep. 2024; 2024: rjae475.
- Rashidi F, Samimiat A, Jafarimehrabady N, Hajebi R. Idiopathic omental hemorrhage: a case report and review of the literature. J Med Case Rep. 2023; 17: 368.
- Tan MNA, Ang WW, Bundele MM, Ong CYG. Omental venous malformation: a rare cause of spontaneous haemoperitoneum. BMJ Case Rep. 2022; 15: e252250.
- Lyu YX, Cheng YX, Li T. Spontaneous omental bleeding: a case report and literature review. BMC Surg. 2018; 18: 33.